

Answer Summary
DME providers can scale in 2026 without sacrificing compliance, quality, or cash flow by using structured partner networks and selective outsourcing. Sustainable growth depends on standardized workflows, defined governance, and clear accountability—because regulatory responsibility always remains with the supplier, regardless of who performs the work.
Introduction: Why Scaling Feels Riskier Than Ever
For many DME providers, growth once followed a predictable formula: add staff, expand locations, and increase volume. In 2026, that approach often introduces more risk than reward.
Providers are now operating in an environment shaped by:
- Persistent labor shortages
- Rising wage and benefit costs
- Increased payer scrutiny and utilization management
- More aggressive pre- and post-payment reviews
- Expanding documentation and authorization requirements
As volume increases, small inconsistencies become systemic problems. Denials rise. Billing slows. Compliance exposure grows quietly until an audit, recoupment, or cash-flow disruption forces attention.
Scaling today is less about getting bigger and more about getting structurally stronger. Partner networks and outsourcing can support that goal—but only when applied deliberately and governed correctly.
What “Scaling” Actually Means in 2026
True scaling is not measured by how much work gets done. It is measured by how well performance holds as volume increases.
Effective scaling means:
- Revenue grows faster than operating costs
- Documentation and billing standards remain consistent
- Audit readiness is preserved across all teams
- Leadership maintains visibility and control
When growth requires constant firefighting, the organization is expanding faster than its processes can support.
The Two Primary Scaling Levers: Partner Networks vs. Outsourcing
Although often discussed together, partner networks and outsourcing serve different strategic purposes and introduce different risks.
Partner Networks
Partner networks typically support:
- Geographic expansion
- Referral growth
- Specialized or complementary services
- Shared infrastructure or expertise
These relationships are often revenue-facing and patient-visible.
Outsourcing
Outsourcing typically supports:
- Billing and A/R follow-up
- Intake processing
- Documentation review
- Administrative back-office functions
These relationships are operationally critical but less visible to patients.
Understanding the distinction matters because governance requirements differ.
Where Partner Networks Create Value
When structured properly, partner networks allow DME providers to:
- Extend service coverage without large capital investment
- Respond faster to referral demand
- Fill service gaps without building new internal departments
For example, a provider may partner with:
- Regional delivery services
- Specialty equipment suppliers
- Referral or service coordination entities
These partnerships can accelerate growth—but they also introduce variability that must be managed.
The Hidden Risk of Informal Partnerships
Many partnership failures do not surface until an audit or payer review.
Common issues include:
- Inconsistent documentation standards
- Unclear responsibility for record retention
- Data-sharing practices that violate internal policy
- Mismatched compliance expectations
From a regulatory standpoint, inconsistency is risk. CMS and commercial payers evaluate outcomes—not intent.
Governance Essentials for Partner Networks
Before scaling through partners, DME providers must formally define:
- Scope of Services—What the partner does and does not do
- Documentation Responsibilities—Who creates, stores, and retrieves records
- Data Access and Security—How patient and billing data is protected
- Compliance Accountability—Who owns failures (still the supplier)
- Performance Metrics – Accuracy, timeliness, and consistency
- Termination Criteria—How to disengage without operational damage
Under 42 CFR § 424.57, DMEPOS suppliers retain responsibility for compliance regardless of delegation.
Outsourcing: Where It Works—and Where It Fails
Outsourcing is most effective when applied to repeatable, well-defined tasks.
High-Success Outsourcing Functions
- Claim submission and status tracking
- Routine A/R follow-up
- Eligibility and benefit verification
- Intake data entry using standardized checklists
These functions benefit from consistency and volume efficiency.
Where Outsourcing Breaks Down
Outsourcing often fails when:
- Workflows are poorly documented
- Exception handling is unclear
- Quality metrics are not enforced
- Oversight is inconsistent
Outsourcing does not eliminate responsibility—it transfers execution while retaining liability.
The Financial Reality of Scaling: Cost Curves, Margins, and Break-Even Risk
Scaling decisions often look profitable on paper but behave differently in execution.
One of the most common leadership mistakes is assuming increased volume automatically improves margin. In reality, scaling introduces nonlinear cost behavior.
For example:
- Staffing costs increase in steps, not increments
- Outsourcing fees rise when exception rates increase
- Partner rework consumes hidden internal labor
A provider that grows volume by 20% may see:
- Only a 10% increase in net collections
- Disproportionate growth in denial-related labor
- Longer A/R cycles due to coordination delays
This is why scaling must be evaluated using capacity curves, not simple revenue projections.
Multi-Location Scaling: Where Variability Becomes Compliance Risk
As organizations scale across locations, variability increases.
Even small differences lead to:
- Inconsistent documentation standards
- Uneven authorization workflows
- Divergent billing practices
Auditors evaluate patterns across the organization, not locations individually.
Effective multi-location scaling requires:
- Centralized policy ownership
- Standardized intake and billing checklists
- Shared dashboards and KPIs
- Clear escalation paths
Without these controls, growth magnifies exposure.
Vendor and Partner Risk Management: From Trust to Verification
Trust is not a control strategy.
High-performing organizations formalize vendor governance using:
- SLAs tied to accuracy and compliance
- KPIs reviewed monthly
- QA sampling of vendor work
- Defined escalation and remediation paths
- Termination readiness plans
If leadership cannot answer, “How do we know vendor work is compliant?” the organization is exposed.
Failure Case Analysis: What Happens When Scaling Is Rushed
Common outcomes of rushed scaling include:
- Increased denials due to intake variability
- Delayed billing from documentation divergence
- A/R spikes caused by coordination breakdowns
- Audit findings tied to inconsistent record retention
These failures rarely stem from bad intent. They result from underestimating complexity.
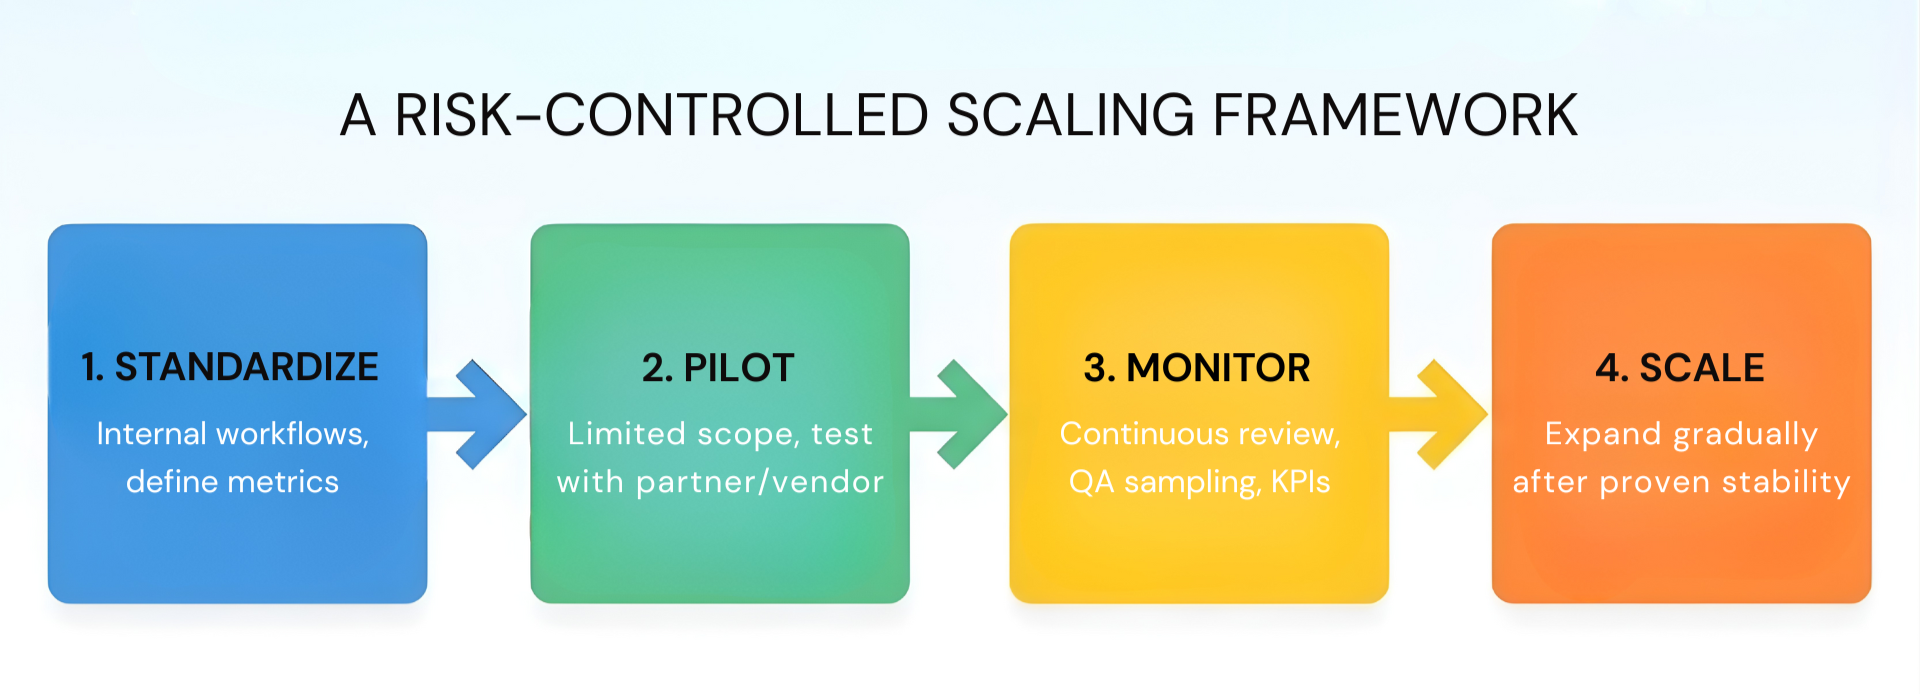
A Risk-Controlled Scaling Framework
Successful DME providers follow a predictable progression:
- Standardize internal workflows
- Define performance metrics
- Pilot with limited scope
- Monitor continuously
- Expand only after stability is proven
If scaling feels chaotic, the foundation is not ready.
Executive Go/No-Go Checklist
Before scaling, leadership should answer:
Operational
- Are workflows standardized across teams?
- Can quality be measured consistently?
Financial
- Do we know the true cost per claim?
- Have break-even scenarios been modeled?
Compliance
- Are audit trails intact across vendors?
- Is responsibility explicit after delegation?
If more than two answers are “no,” scaling should pause.
How Wonder Worth Solutions Helps
Wonder Worth Solutions helps DME providers scale responsibly by:
- Standardizing workflows before expansion
- Aligning partner and vendor performance with compliance expectations
- Designing governance models that protect revenue and audit readiness
The focus is sustainability—not speed.
Authoritative Resources Referenced
- 42 CFR § 424.57—DMEPOS Supplier Standards
- CMS Medicare Program Integrity Manual
- CMS MLN Matters: Supplier Compliance Guidance
- AAHomecare Operational Best Practices
Conclusion
In 2026, scaling that weakens control is not growth—it is deferred risk. DME providers that use partner networks and outsourcing deliberately, with strong governance and standardized workflows, can grow confidently without increasing compliance or financial exposure.

